

- The pharmaceutical industry is one of India’s oldest industries and stands at the top among its science-based industries, with wide skills in the complex field of drug manufacture and technology.
- India is known as the “Pharmacy of the World”. It is the largest supplier of generic medicines, with about 20% of global supply.
- It is among the most organised sectors in India. Low-cost plants, educated and skilled manpower and cheap labour have lifted its production, development and research, and its role in global medicine.
Growth and Structure
From Import Dependence to Scale
- Growth here is largely a post-Independence story. Before 1947, the bulk of drugs came from abroad, and only processing and formulation happened in India.
- Growth ran at about 10% a year for over three decades.
- Older claims held that India met over 95% of its bulk drug needs and was self-sufficient in formulations. Production spans antibiotics, vitamins, steroids, hormones, semi-synthetic penicillins, phytochemicals and biological products.
- Bulk drug self-sufficiency has since slipped. Imports, mostly from China, now fill much of the gap.
- India grew into a major exporter to third-world countries, and now also sells heavily in regulated markets.
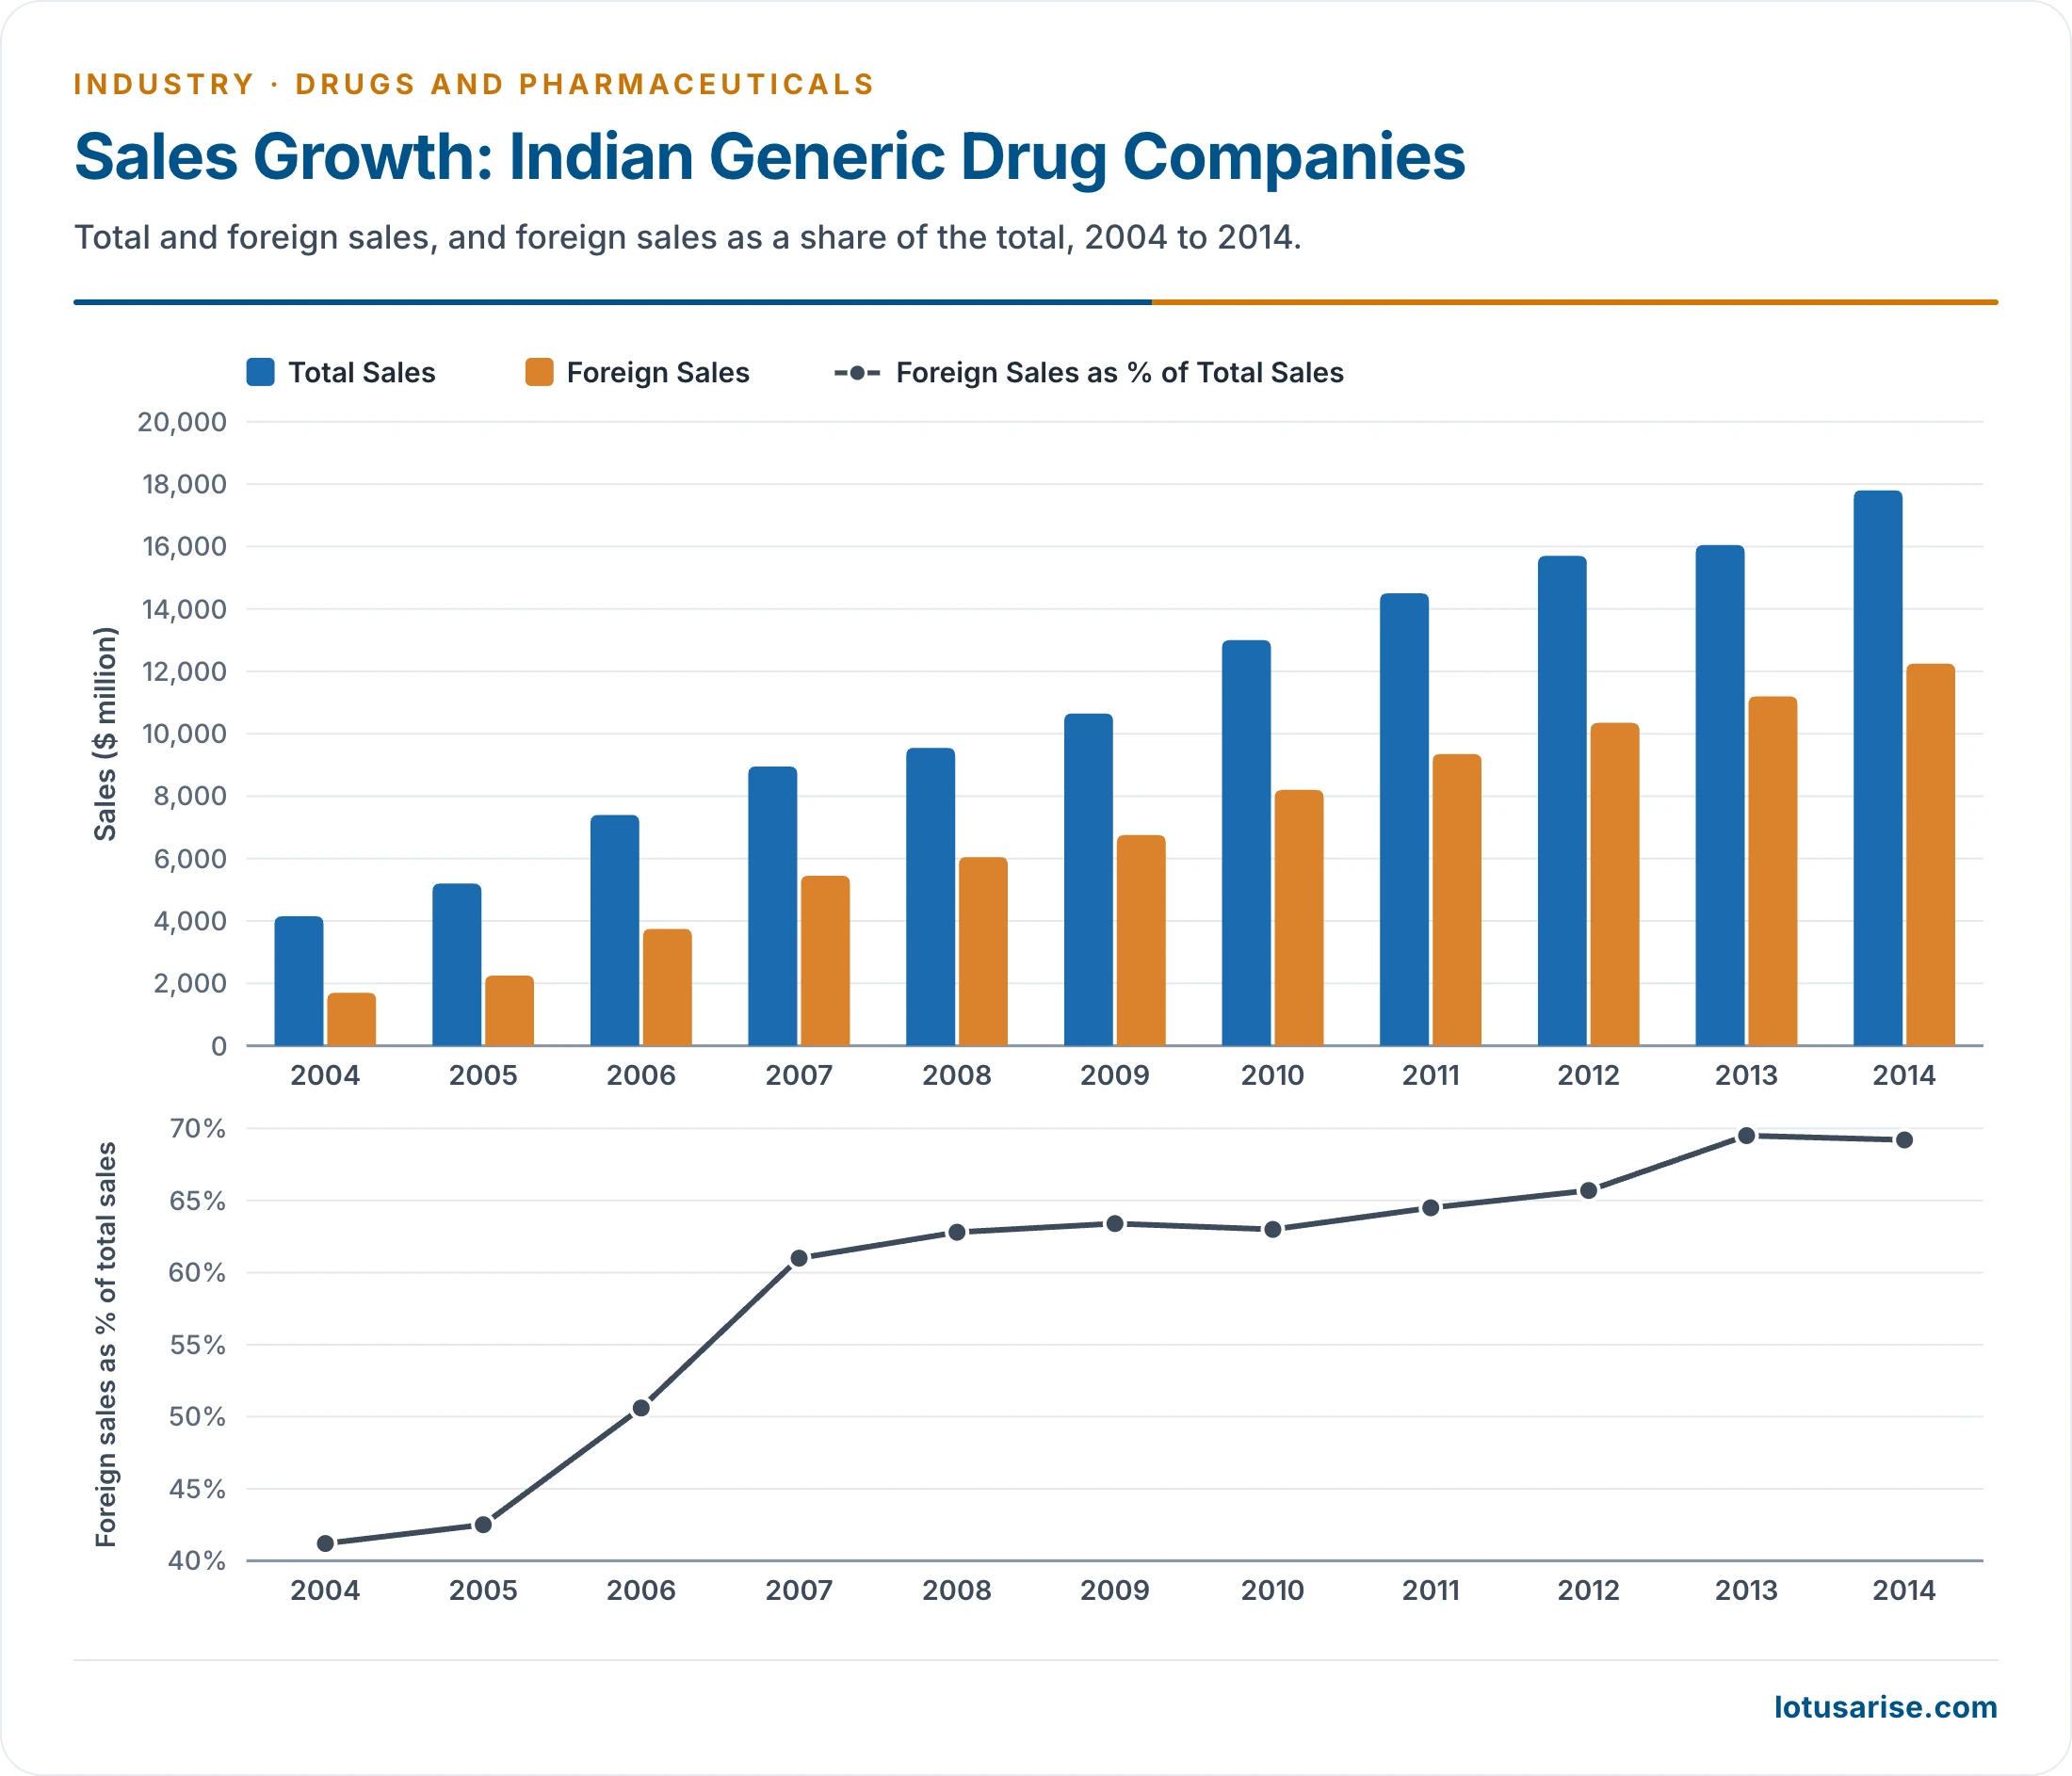
- This chart stops at 2014, when foreign sales had reached nearly 70% of the total for these firms. Exports reached US$30.5 billion in 2024-25.
Scale Today
| Measure | Older account | Latest |
|---|---|---|
| Global rank | Third by volume | Third by volume, 11th by value (14th by value earlier) |
| Firms | About 250 major units and thousands of small ones | Over 3,000 companies and 10,500 units |
| Domestic market | About 75% of demand met by local makers | US$60 billion, projected at US$130 billion by 2030 |
| Turnover | Rs 4.72 lakh crore (2024-25) | |
| Exports | Third-world focus | US$30.5 billion to 191 countries (2024-25), half to regulated markets |
- Export pace: US$1.9 billion in 2000-01, and US$28.29 billion in April–February 2025-26, up 5.6%. The USA took 34% of that.
- An older KPMG estimate put the organised sector at 250–300 companies with 70% of the market, the top ten holding 30%. The whole sector ran to nearly 20,000 businesses, some very small.
- An older official break-up:
- About 250 organised units: five public, six joint-sector, 21 under the Monopolies and Restrictive Trade Practices Act and six under the Foreign Exchange Regulation Act. Both Acts have since been replaced.
- About 5,000 small units, over 100 of them making bulk drugs.
- Other strengths in 2026:
- About 500 makers of active pharmaceutical ingredients (APIs), with nearly 8% of the global API industry.
- The largest number of plants approved by the US Food and Drug Administration outside the USA.
- About 60,000 generic brands across 60 therapeutic categories.
- Vaccines: about 60% of UNICEF’s supplies, 40–70% of global demand for DPT and BCG, and 90% of the WHO’s measles vaccine demand.
- Product pattern: antibiotics long led sales, while diabetes, cardiovascular and central nervous system treatments grew fastest.
- Access: modern drugs were once said to reach only 40% of Indians, mainly in urban areas. Jan Aushadhi Kendras now number over 18,646 (February 2026).
Distribution and Location
Major Regions
- The industry has emerged mainly in six regions:
| Region | Centres |
|---|---|
| Mumbai–Ahmedabad–Pune (about 60% of output in older estimates) | Mumbai, Ahmedabad, Pune, Surat, Vadodara, Bharuch, Pimpri |
| Hugli | Kolkata, Hugli |
| Chennai–Coimbatore–Bengaluru | Chennai, Coimbatore, Bengaluru |
| Hyderabad–Secunderabad | Hyderabad, Secunderabad |
| Delhi | Delhi and its surrounding towns, Gurugram among them |
| Indore–Gwalior | Indore, Gwalior |
- Scattered centres: Kanpur, Lucknow, Rishikesh and Bhubaneswar.
- Small units gather most heavily at Mumbai, Chennai, Kolkata, Delhi, Vadodara, Kanpur and Hyderabad.
- A 2023 official survey counted 118 clusters in 19 States and Union Territories, with 7,673 units. Maharashtra led with 40 clusters.
- Output shares (NITI Aayog Trade Watch, January–March 2026): Gujarat about one-third or more, and Maharashtra 14%.
- Newer belts:
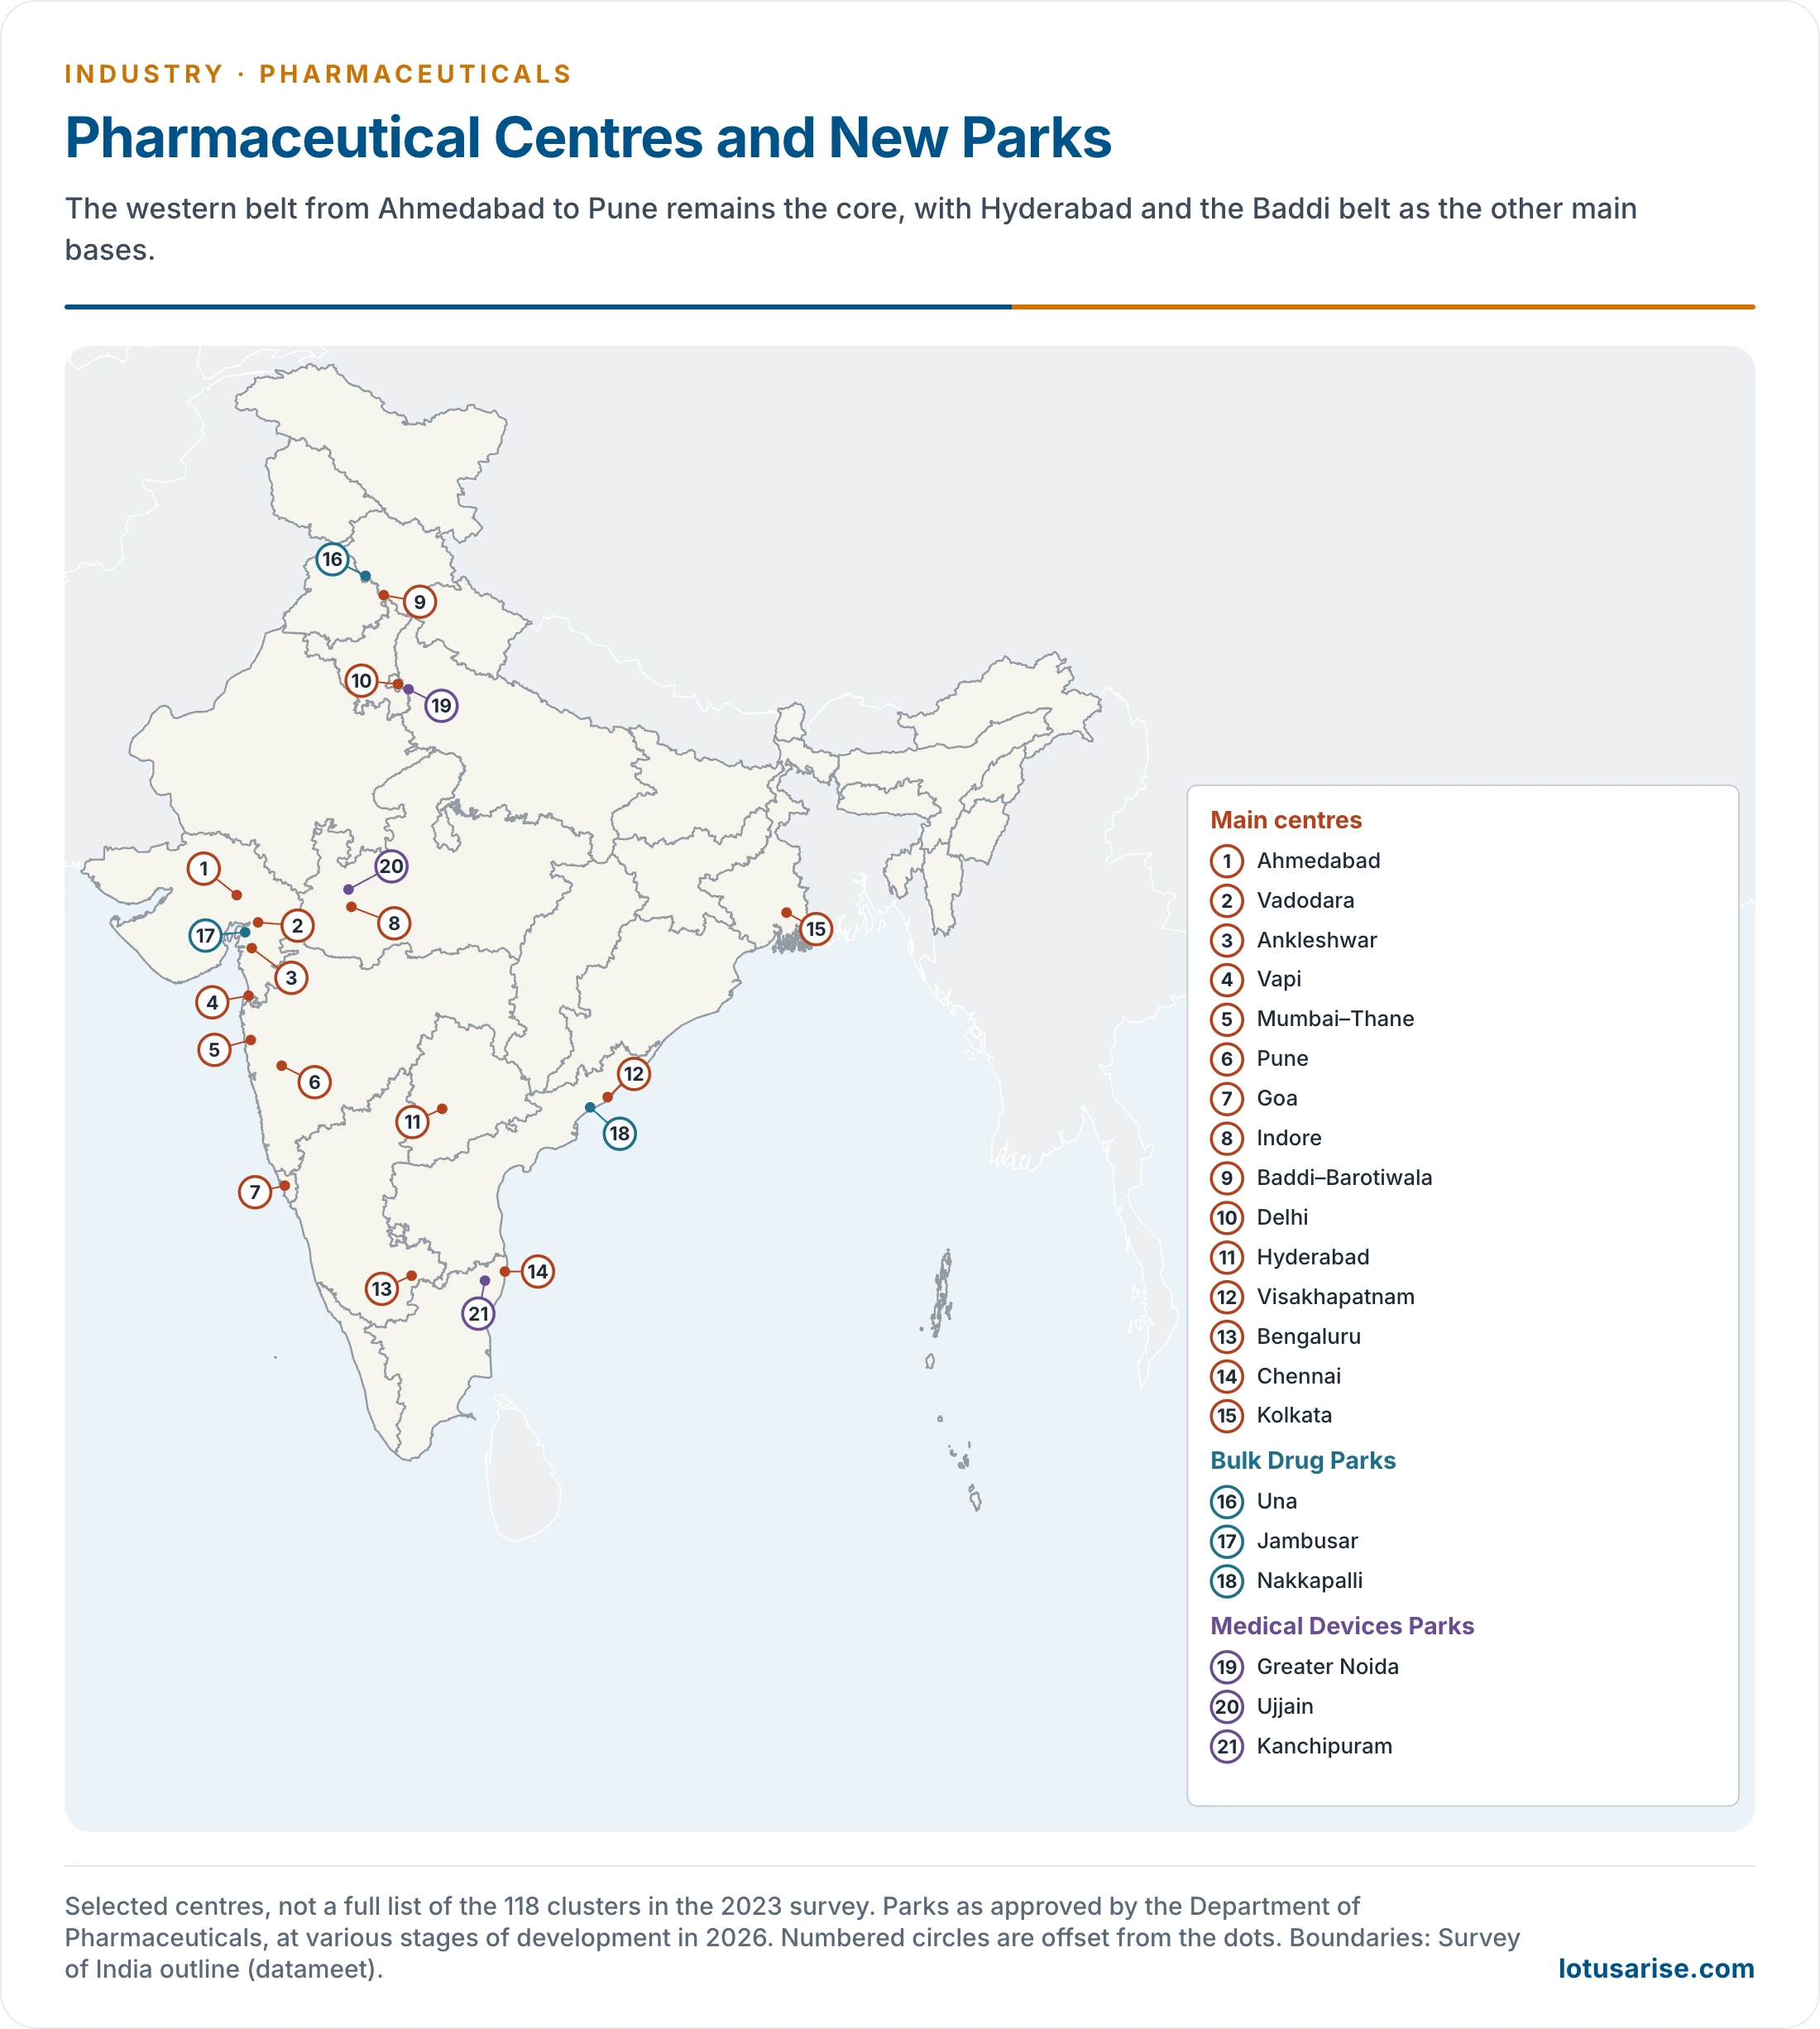
- Baddi–Barotiwala in Himachal Pradesh is the main northern belt.
- Hyderabad leads in vaccines and biotechnology.
- Visakhapatnam is the east coast base.
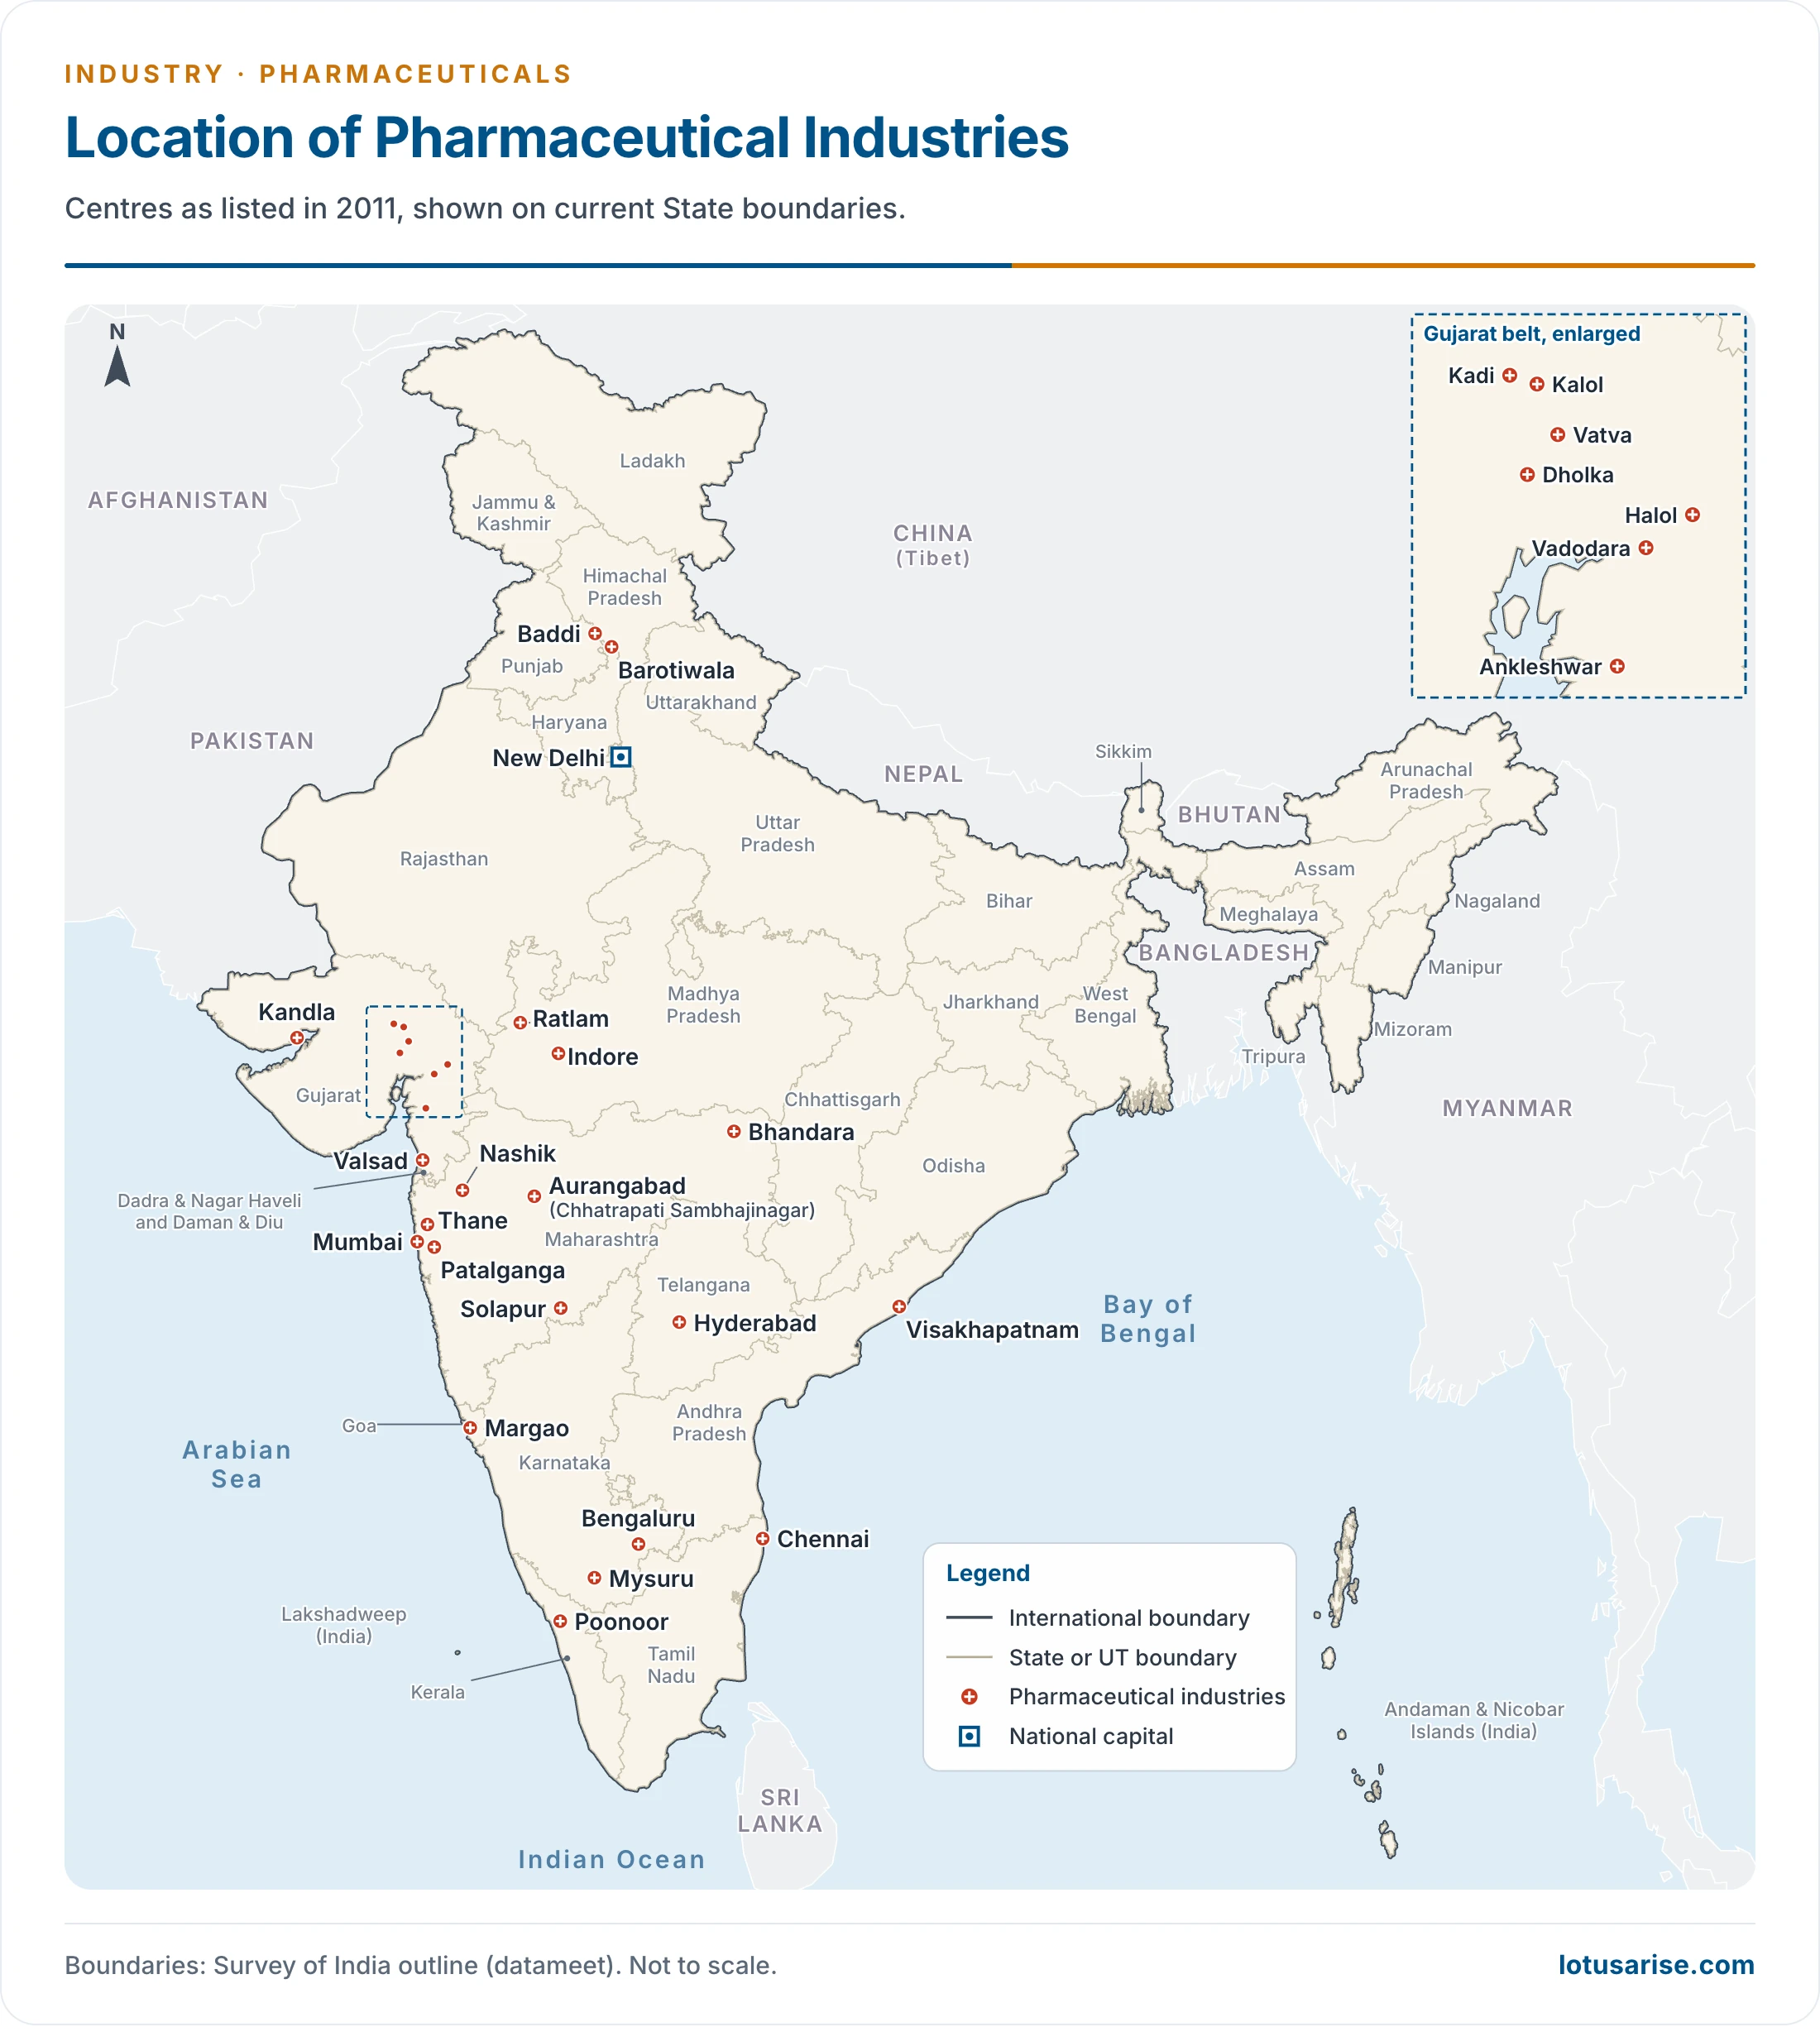
- Hirapur in Gujarat is also on the 2011 list.
Location Factors
- Market:
- The domestic market is huge, and the push for generic medicines has strengthened it.
- Africa has long been a key buyer of Indian generics. West coast plants cut transport costs to Africa and Europe.
- Government policy:
- Foreign direct investment (FDI) is allowed up to 100%: automatic for new plants, and automatic up to 74% in existing ones, with approval beyond that.
- The Patents Act, 1970 let the industry grow on its own terms.
- Supreme Court, 1 April 2013: Novartis v. Union of India applied Section 3(d) against evergreening.
- Compulsory licensing, March 2012: under Section 84, the Controller of Patents licensed Bayer’s Nexavar to Natco. Bayer’s later challenges strengthened the confidence of Indian firms against foreign conglomerates.
- Biotechnology has grown fast over 25 years, and tax incentives support research and development. Ranbaxy’s research base was one such case before it merged into Sun Pharma of Mumbai in 2015.
- Infrastructure: power, transport and communication matter. Most output sits on the west coast for infrastructure and market reasons.
- Labour skills: skilled workers shape location, and their spread explains the industry’s decentralisation.
- Raw materials: nearness to petrochemical hubs, such as Jamnagar in Gujarat and Bombay High off Maharashtra, and to the chemical industry around Vadodara and Ankleshwar.
- Capital: western India has long been the hub of trade and capital.
Why the West Leads
- The factors above meet in one belt, from Ahmedabad and Vadodara through Ankleshwar and Vapi to Mumbai, Thane and Pune.
- Old commerce came first. Mumbai’s capital, ports and early firms gave the region a head start in processing and formulation.
- A chemical base followed. Gujarat holds about a third of India’s chemical output, so solvents and intermediates are close at hand, and Dahej adds a large petrochemical supply.
- Ports then tied the belt to exports. Shipments to Africa, Europe and the USA leave more cheaply from the west coast.
- Skilled labour and a wide supply of contract makers keep new firms in the same towns.
- Other centres have grown for their own reasons. Hyderabad has drawn on public-sector skills from the IDPL plant, and Baddi–Barotiwala has grown as a newer northern belt.
Public and Private Sectors
Public Sector
| Company | Founded | Base and products | Position now |
|---|---|---|---|
| Indian Drugs and Pharmaceuticals Limited (IDPL) | 5 April 1961 | Five plants: Rishikesh (antibiotics), Hyderabad (synthetic drugs), Gurugram (formulations), Chennai (surgical instruments), Muzaffarpur (drugs and chemical intermediates) | Closure decided in December 2016 |
| Hindustan Antibiotics Limited (HAL) | 10 March 1954 | Pimpri, with WHO and UNICEF help: Penicillin, Streptomycin, Amoxicillin, Hamycin, Gentamycin, Aureofungin, and formulations | Sick since 1997; strategic sale decided |
| Smith Stanistreet Pharmaceuticals (SSPL) | Nationalised sick unit | Kolkata: formulations | |
| Bengal Chemicals and Pharmaceuticals (BCPL) | Works of 1901; company of 1981 | Maniktala and Panihati (West Bengal), Kanpur, Mumbai; largest maker of anti-snake venom in older accounts | Strategic sale decided |
| Bengal Immunity (BIL) | Nationalised sick unit | Baranagar: anti-malarial drugs and vaccines | Long closed |
- Bengal Chemical began with Acharya Prafulla Chandra Ray. The government took over its management in 1977 and nationalised it on 15 December 1980.
- IDPL’s joint companies with State governments:
- Rajasthan Drugs and Pharmaceuticals (RDPL), Jaipur.
- Uttar Pradesh Drugs and Pharmaceuticals (UPDPL), Lucknow.
- Orissa, now Odisha, Drugs and Chemicals (ODCL), Bhubaneswar.
- HAL’s joint companies:
- Maharashtra Antibiotics and Pharmaceuticals (MAPL), Nagpur.
- Karnataka Antibiotics and Pharmaceuticals (KAPL), Bengaluru.
- Manipur State Drugs and Pharmaceuticals (MSDPL), Imphal.
- Many other units were set up with State governments.
- The Cabinet’s December 2016 decision: sell surplus land to clear liabilities, close IDPL and RDPL, and sell HAL and BCPL. KAPL’s disinvestment was added in 2017.
- These firms have lost their old lead: the private sector and exports now drive the industry.
Private Sector and the Patent Regime
- Patents Act, 1970:
- It gave only process patents for pharmaceutical and agrochemical products.
- A strong generic industry arose, making the drugs of multinational companies at low prices. Cipla and Ranbaxy made HIV/AIDS drugs far cheaper.
- Countries unable to afford multinational prices turned to these drugs.
- Patents (Amendment) Act, 2005:
- It brought product patents for food, chemicals and pharmaceuticals, meeting India’s duty under the TRIPS Agreement of the WTO.
- India accepted this because TRIPS came with the wider WTO package, its pharmaceutical firms were going global, and patents could help research.
- The sector became globally competitive.
- Industrial liberalisation after 1991:
- Licensing ended and all segments were de-reserved.
- FDI up to 74% was allowed, and plants making new drugs through in-house research were freed from price control.
- Many medium and small firms arose in Mumbai, Pune, Ahmedabad and Hyderabad.
- Features of these firms:
- Many are export-oriented.
- They attracted investment from non-resident Indians.
- Players such as Dr. Reddy’s set up research units.
- They make new drugs cheaply and compete with multinationals.
- They hold a large market in developing nations.
- It is regarded as a sunrise industry.
- Older leading names included Ciba, Sarabhai, Hoechst, Alembic, Glaxo, Unichem, Pfizer, Chemo Pharma and Warner Hindustan.
- Foreign investment rules eased further under the Pharmaceutical Policy, 2002, which allowed FDI up to 100% subject to conditions, and automatic approval for foreign technology agreements.
Regulation and Prices
- The National Pharmaceutical Pricing Authority fixes and revises prices under the Drugs (Prices Control) Order, 2013. Earlier policy kept newly developed drugs outside price control for a set period, to reward research at home.
- The Central Drugs Standard Control Organisation is the national regulator, under the Drugs and Cosmetics Act, 1940. It handles new drug approvals, clinical trials, licences for imports and manufacture, and safety monitoring.
- The Indian Pharmacopoeia Commission publishes the official drug standards, and 19 countries recognise them.
Problems and Prospects
Problems
- Technology: India lags other WTO members in research for new medicines, and focus on innovation has been limited.
- Raw material deficit:
- India supplies quality medicines to many countries, yet leans heavily on China for Active Pharmaceutical Ingredients (APIs), or bulk drugs.
- Chinese scale and lower costs drew Indian formulators away from making many of these inputs at home, so the risk sits at the start of the chain.
- This makes supply sensitive to the state of Indo-Chinese relations, even though India exports finished medicines worldwide.
- China’s share of these imports has been about 70%, at 70–74% in trade analyses.
- In March 2026 the Department of Pharmaceuticals listed for Parliament the APIs where China supplied 70% or more.
- Competition:
- Firms in China, Israel and Japan press hard.
- Large foreign players often accuse Indian firms of breaching patent law.
- Patent grants surged after the 2005 TRIPS changes, then waned as the intellectual property climate weakened.
- Adulteration and piracy: duplicate makers have mushroomed. In October 2025, the Coldrif cough syrup, contaminated with diethylene glycol, killed children in Madhya Pradesh.
- US pressure: the Special 301 Report of the US Trade Representative kept India on its Priority Watch List again in 2026.
- Volume over value: third by volume but 11th by value shows reliance on low-margin generics.
- Moving up means complex generics, biosimilars and new molecules, which need more research money and longer patience.
- Under the Scheme for Promotion of Research and Innovation in Pharma MedTech, seven Centres of Excellence at the national institutes had 111 approved projects by November 2025, with an outlay of Rs 700 crore.
- Market risk: the USA is the largest single buyer, so US tariff decisions and price pressure matter. Its share slipped to about 31% in April–June 2026-27.
Prospects
- Costs: among the lowest in the world, below the USA and nearly half of Europe’s.
- Skills: skilled labour remains a driver and spreads the industry.
- Traditional medicine: government promotion brightens its outlook.
- Demand: life-saving drugs are in huge demand at home and abroad. India was expected to reach the top three markets by incremental growth in 2020.
- Generics: India’s lead as the largest provider gives it global standing.
- Research: laboratories and biotech parks add competitiveness.
- Contract research:
- A Contract Research Organisation, or Clinical Research Organisation, gives outsourced research services to pharmaceutical and biotechnology firms, for drugs and medical devices.
- Indian firms are active in this with foreign partners.
Policy Since 2020
- Production Linked Incentive (PLI) for pharmaceuticals: Rs 40,890 crore invested against a target of Rs 17,275 crore, by September 2025.
- PLI for bulk drugs: capacity of 55,100 tonnes a year for 26 critical APIs, by September 2025.
- Bulk Drug Parks: Una (Himachal Pradesh), Jambusar in Bharuch (Gujarat) and Nakkapalli (Andhra Pradesh), with Rs 1,000 crore of central help each.
- Medical Devices Parks: Greater Noida, Ujjain and Kanchipuram, with 199 makers allotted land by December 2025. Device exports rose from US$2.5 billion in 2020-21 to US$4.1 billion in 2024-25.
- Market access: the India–UK trade agreement (July 2025) gives zero duty on 56 pharmaceutical tariff lines, and the New Zealand agreement covers about 90. Exporters are also spreading to Nigeria, Mexico, Tanzania, Brazil and Saudi Arabia.
- Affordable access: the Pradhan Mantri Bhartiya Janaushadhi Pariyojana sold Rs 2,022 crore of generics in 2024-25, with estimated savings of about Rs 8,000 crore for buyers.
- Biopharma SHAKTI (2026-27): Rs 10,000 crore over five years for biologics and biosimilars, with three new National Institutes of Pharmaceutical Education and Research and 1,000 clinical trial sites.
The Way Ahead
- The 2005 patent regime brought back multinationals, many of which left India in the 1970s. They now look to India for contract manufacturing, research and clinical trials.
- Indian firms are becoming global players, and some out-compete established brands.
- Health consciousness is rising. The need is to disperse the industry further and lower manufacturing costs.
- Institutions such as the National Institute of Pharmaceutical Education and Research (NIPER), now seven in number, can help make India a key global player.
Previous Year Questions
2025Explain the factors which contribute to the growth of India’s pharmaceutical industry with specific reference to its concentration in western region of India.2023The Indian pharma industry has to move from ‘volume’ to ‘value’ leadership to capture the global market. Discuss.2020The pharmaceutical industry in India depends on the import of raw material. Evaluate this statement in view of the Indo-Chinese relationship.2015Why does the pharmaceutical industry concentrate largely in the western region of the country?2011Assess the scope and development of Pharmaceutical industry in India.





Thanks alot
Thank a lot it helps me to understand the topic very clearly