

- A population policy is a set of deliberate measures by which the state tries to influence demographic change: the number of births, the level of mortality, the volume and direction of migration, and the distribution of people over its territory.
- Its aims may be quantitative (size, growth rate, age structure) or qualitative (health, education, gender equity, the composition and skills of the population).
- Policies arise as a response to the consequences of fertility, mortality and migration trends. Rapid growth strains resources; very low fertility brings ageing and shrinking workforces; migration changes the size, make-up and spread of a population.
Rationale for Population Policy

The State and the Public Good
- The state exists to serve collective interests and provide public goods: security, justice, welfare and a sound environment. Population size, growth and structure affect every one of these.
- In India, the goals in the Preamble of the Constitution (justice, liberty, equality and the welfare of the people) depend on demographic trends as much as on economic ones.
- Population policy is therefore a tool of governance: it tries to keep demographic change in step with development goals.
Scientific Management of Population
- Governments study past and present demographic trends and project future ones. This allows them to:
- Judge whether population is moving towards or away from an optimum relative to resources.
- Plan schools, hospitals, housing, jobs and pensions for the population that will exist, not the one that existed.
- Balance population with sustainable use of land, water and energy.
- Projections give long lead times. The workers of 2045 and the pensioners of 2060 are already born.
Three Components, Three Levers
- Any change in population comes from fertility, mortality and migration. Policy can act on each:
- Fertility: birth rates and reproductive behaviour.
- Mortality: death rates and health.
- Migration: movement across and within borders.
- Together they decide the size, structure and spatial distribution of a population, so a full policy considers all three.
Private Decisions with Public Consequences
- Migration control, above all of immigration, is clearly a public matter: it affects labour markets, public finances, security and social cohesion.
- Fertility is a private decision with public consequences:
- High fertility strains schools, health services, jobs and the environment. This was the classic concern of Thomas Robert Malthus (1798) and of the neo-Malthusian writers of the 1960s and 1970s.
- Low fertility produces an ageing population, labour shortages and pressure on pensions and health care.
Externalities
- Families decide on children by weighing their own costs and benefits: economic, social and cultural.
- These decisions create externalities, effects on others that the family does not bear or receive:
- Costs fall on the public: services, unemployment, pressure on common resources (the “tragedy of the commons” of Garrett Hardin, 1968).
- Benefits also accrue to the public: future workers and taxpayers who pay for everyone’s pensions.
- Because private and social costs differ, the state intervenes to bring private choices closer to the social optimum, through incentives, information and services rather than force.
From Control to Choice
- Policy has moved from “population control” to rights-based population management:
- Bucharest (1974): the first World Population Conference adopted a World Population Plan of Action. India argued that “development is the best contraceptive”.
- Mexico City (1984): family planning was linked more closely to development and health.
- Cairo (1994): the International Conference on Population and Development (ICPD) placed reproductive health and rights, women’s empowerment and education at the centre. Demographic targets were replaced by informed choice.
- Modern policy therefore aims to design institutions and incentives that make individual choices serve collective goals: universal access to contraception and health care, girls’ education, social security, and support for parents.
- Coercion, as in China’s one-child policy and India’s Emergency of 1975–77, is now widely judged a violation of rights and also less effective in the long run.
Three Approaches
| Approach | Core idea | Main instruments | Criticism |
|---|---|---|---|
| Family planning (supply) | Couples have unwanted births because they lack means | Contraceptive supply, targets, incentives | Ignores why people want large families |
| Development (demand) | Fertility falls when children cost more and survive | Education, health, jobs, social security | Slow; needs services too |
| Rights-based (Cairo) | Individuals decide; the state ensures choice and health | Reproductive health, women’s empowerment | Weak where services are poor |
- In practice successful countries combined all three: services to meet existing demand, development to change demand, and rights to protect individuals.
- The supply view dominated the 1950s–70s, when donors and bodies such as the Population Council (founded 1952) promoted family planning programmes to hasten the transition. The demand view gained ground after Bucharest. The rights view has framed global policy since Cairo.
Elements of Population Policy
- Every population policy rests on the three components of change, with spatial distribution as a fourth element. Making one involves:
- Assessing past and present trends.
- Projecting future change.
- Evaluating the socio-economic consequences.
- Designing measures to move demographic behaviour in the desired direction.
- Behaviour differs between regions, classes, castes and communities, so policy must target the determinants in each group.
- In developing countries, policy has focused overwhelmingly on fertility; mortality and migration received less attention, though all three matter.
Fertility
Anti-natalist Policies
- Anti-natalist policies aim to reduce birth rates. They are adopted in high-fertility countries to ease pressure on resources and raise living standards.
- Direct measures:
- Supply of contraceptives and family planning services.
- Liberal abortion laws.
- Raising the legal age at marriage.
- Incentives for small families (cash for sterilisation, priority in jobs or housing) and disincentives for large ones (loss of benefits, bars on public office).
- Indirect measures:
- Female education and women’s employment.
- Maternal and child health, so that more children survive.
- Population education and awareness.
- Social security that reduces dependence on children in old age.
- The most effective programmes changed behaviour through socio-economic transformation and services, not compulsion.
- Examples:
- China: the “later, longer, fewer” campaign (1971) and the one-child policy (1980–2015), enforced with targets, fines and forced procedures.
- India: the world’s first national family planning programme (1952).
- Bangladesh, Indonesia, Thailand and Iran: voluntary programmes with door-step services that cut fertility from 5–7 to about 2.
Pro-natalist Policies
- Pro-natalist policies aim to raise birth rates in low-fertility, ageing societies. Their goals are to slow population decline, avoid labour shortages and keep the age structure balanced.
- Measures:
- Child allowances, tax relief and birth bonuses.
- Paid maternity and paternity leave.
- Subsidised childcare and pre-school.
- Housing and loans for young families.
- Flexible work.
- Examples:
- Sweden: Alva Myrdal and Gunnar Myrdal (1934) argued for a welfare route to population policy: voluntary parenthood, universal contraception and sex education, plus generous support for children. Sweden introduced parental leave for both parents in 1974.
- France: a family code (1939), family allowances and a tax system that rewards larger families. France long had one of the highest fertility rates in Europe.
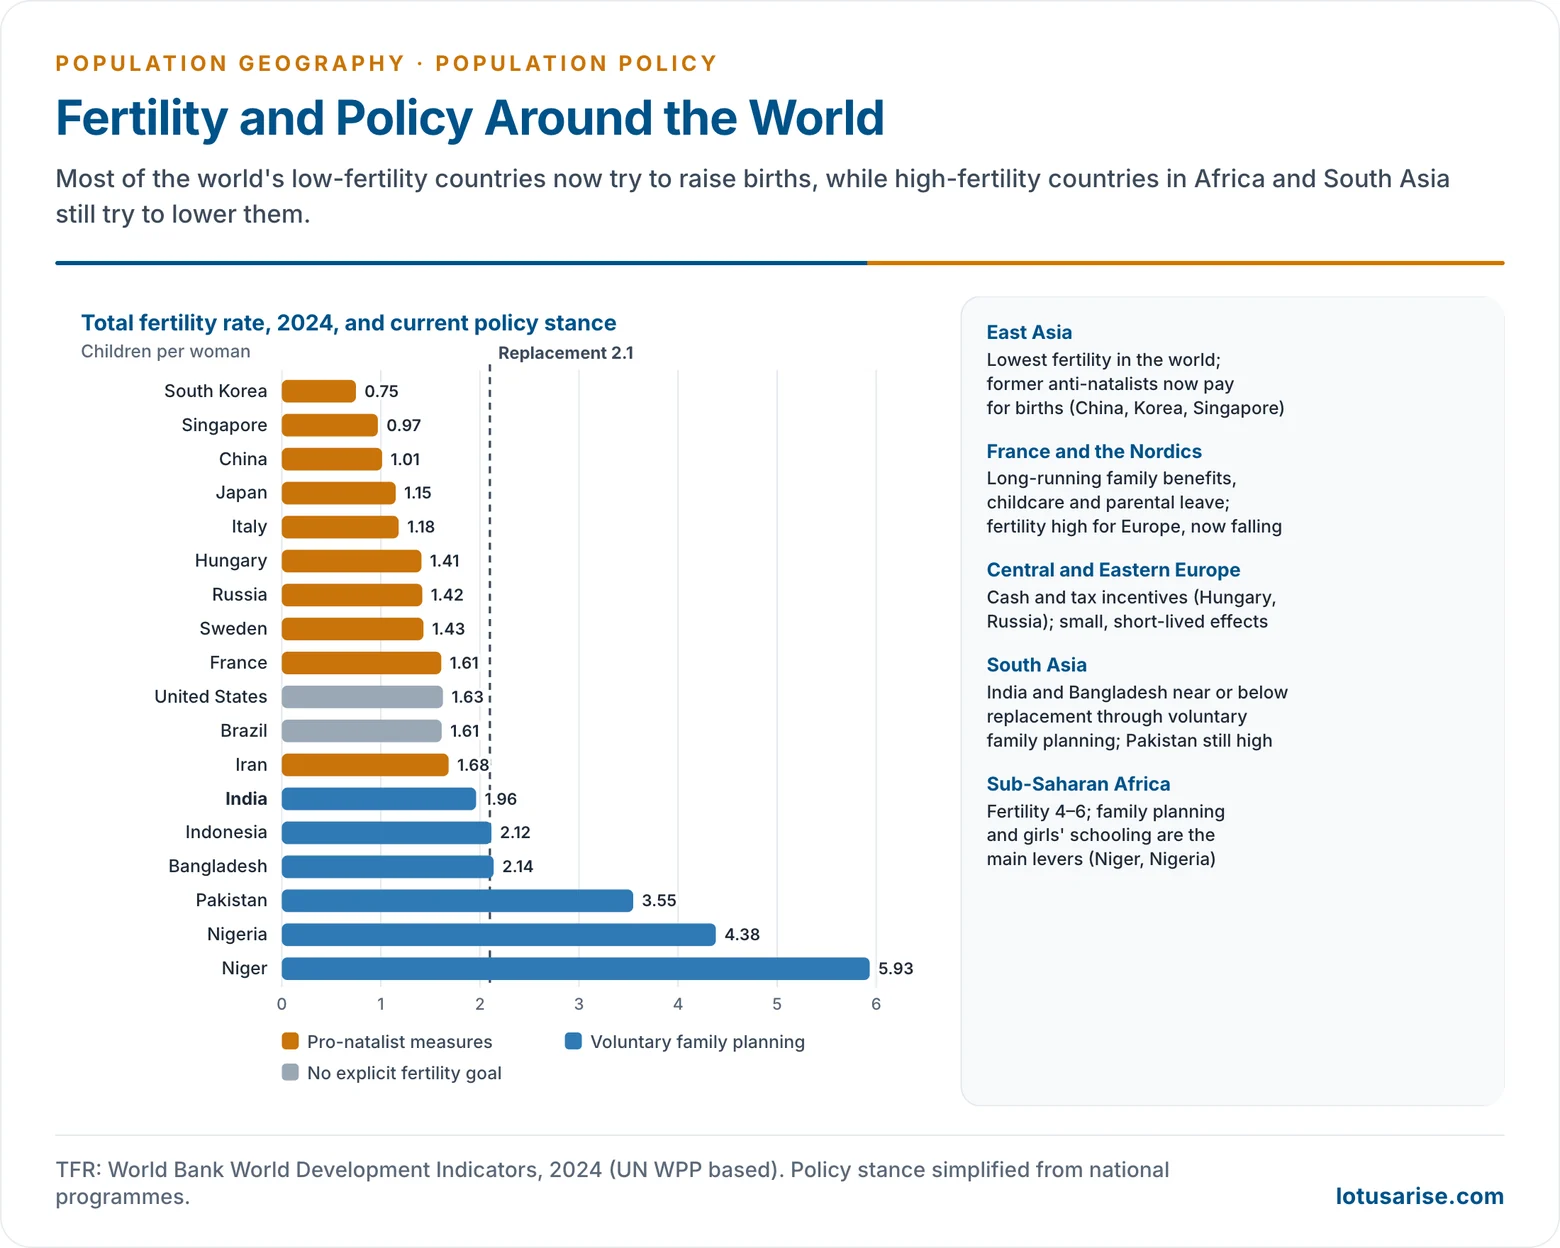
- Japan: fertility fell after abortion was legalised in 1948. Since the “1.57 shock” of 1990 Japan has tried the Angel Plan (1994), childcare expansion and a Children and Families Agency (2023), yet its TFR fell to 1.15 in 2024.
- Hungary and Russia: cash incentives such as Russia’s maternity capital (2007) and Hungary’s lifetime income-tax exemption for mothers of four or more children (2020).
- Romania: Decree 770 (1966) banned abortion and contraception. Births nearly doubled in 1967, then fell back, and maternal deaths rose. It remains the classic warning against coercive pro-natalism.
Mortality
- Mortality policies aim to cut death rates, raise life expectancy and improve the quality of life.
- High-mortality (developing) countries:
- Reduce infant, child and maternal mortality.
- Control communicable diseases, provide safe water and sanitation, and spread immunisation.
- Expand primary health care and nutrition.
- The World Health Organization and UNICEF have played a large part, from smallpox eradication (1980) to vaccine campaigns.
- Low-mortality (developed) countries:
- Health insurance and the quality of care.
- Non-communicable diseases and elderly care.
- Lifestyle risks and road safety.
- Mortality policy is part of human development. It also has a demographic paradox: by saving lives it first accelerates growth, as the demographic transition shows.
Migration
International Migration
- States regulate migration to protect economic, social and political interests:
- Immigration controls: quotas, visas, work permits.
- Selective migration of skilled workers, as in Canada’s points system (1967), Australia after the end of the White Australia policy (1973), Germany’s Skilled Immigration Act (2020) and Japan’s Specified Skilled Worker visas (2019).
- Temporary labour schemes, from Germany’s guest workers (1955–73) to the kafala sponsorship system of the Gulf states.
- Refugee and asylum policies.
- Emigration policies: protecting workers abroad, encouraging remittances and return, and limiting brain drain.
- International conventions and UN agencies (UNHCR, IOM) increasingly shape migrant rights, as the scale of world migration and of refugee flows has grown.
Internal Migration
- Most countries allow free internal movement, but migration is often unplanned, dominated by rural–urban flows.
- Problems:
- Urban congestion and slums.
- Pressure on infrastructure and services.
- Widening regional inequality.
- Measures:
- Regional and urban planning, satellite towns and new growth centres.
- Decentralisation of industry and services.
- Rural development and rural employment to reduce distress migration (India’s MGNREGA, 2006).
- Some states restrict movement: China’s hukou (household registration, 1958) tied social rights to the place of registration and long held back rural–urban migration.
Distribution
- Distribution policies try to change where people live:
- Resettlement and colonisation: Indonesia’s transmigration moved millions from crowded Java to the outer islands; Malaysia’s FELDA (1956) settled landless families on new plantations.
- New capitals and growth centres: Brasília (1960) was built to draw people into Brazil’s interior. Chandigarh, Bhubaneswar and Gandhinagar served similar roles in India.
- Dispersal of industry and incentives for backward regions.
- Such schemes often cost more than expected and caused environmental damage and conflict with local people, as in parts of Indonesia’s outer islands and the Amazon.
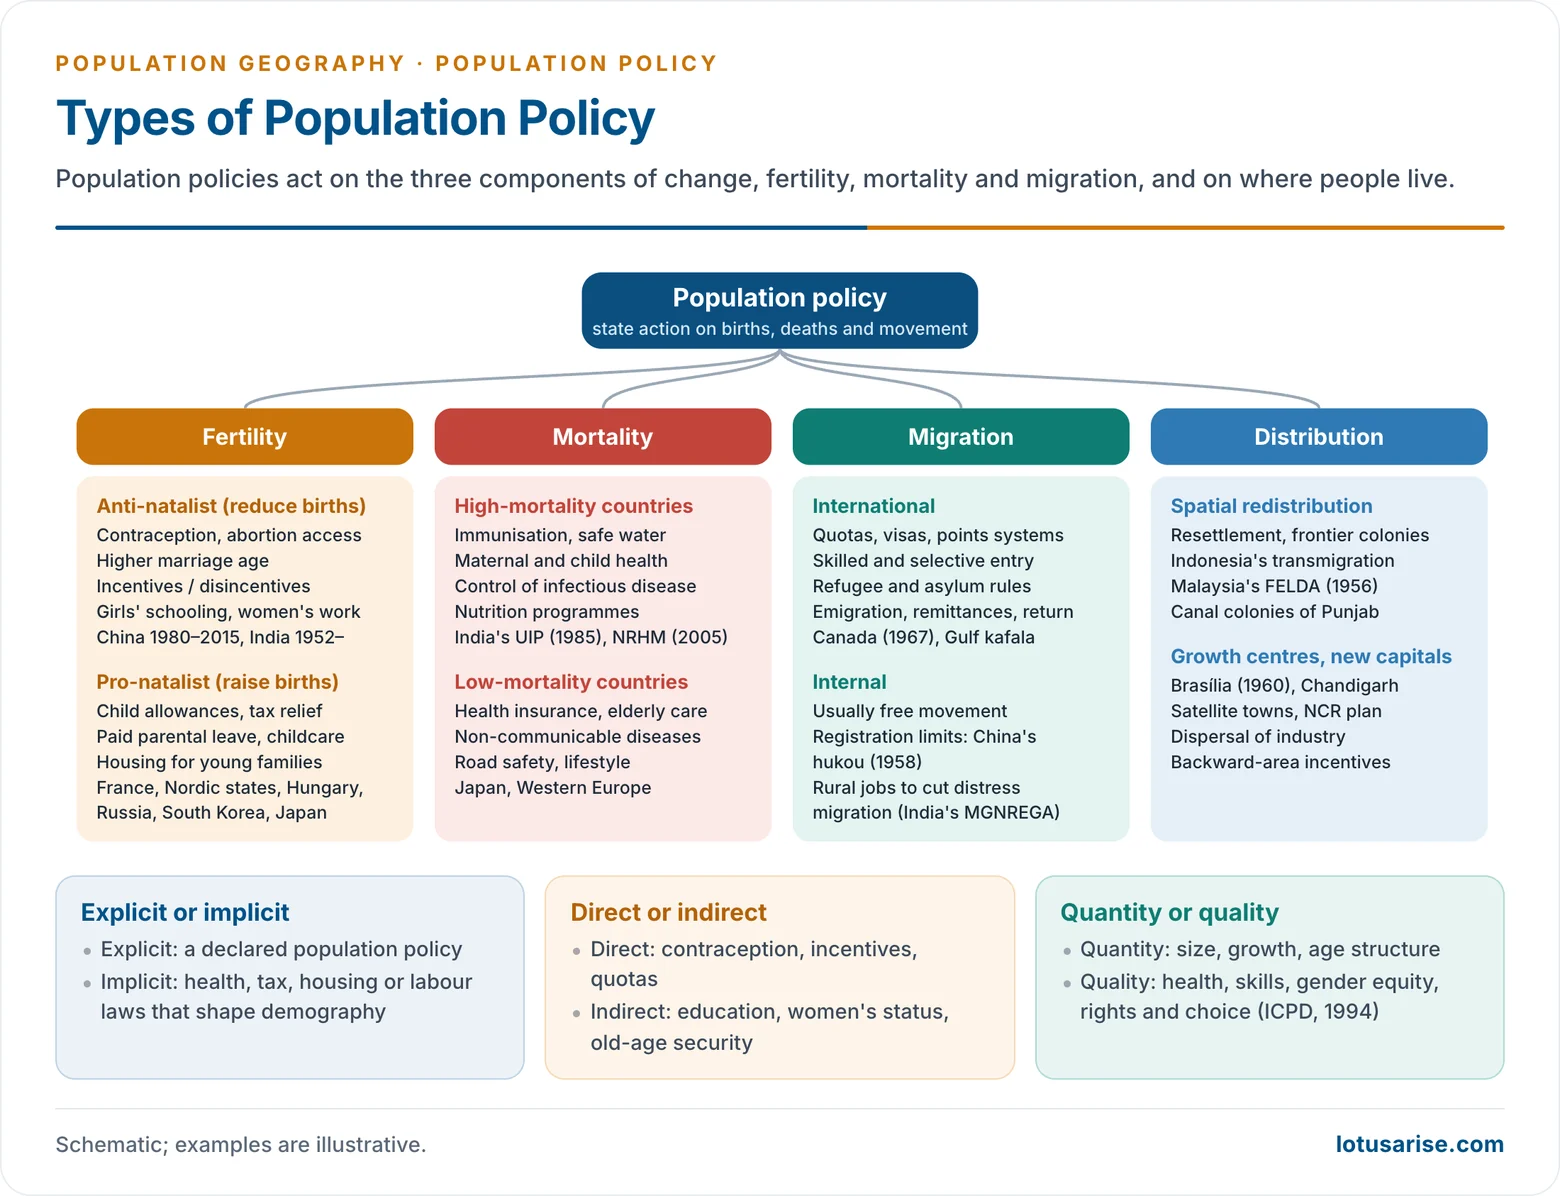
| Element | Aim | Typical measures | Examples |
|---|---|---|---|
| Anti-natalist | Fewer births | Contraception, marriage age, incentives, girls’ schooling | China 1980–2015, India, Bangladesh, Iran 1989 |
| Pro-natalist | More births | Allowances, leave, childcare, housing | France, Sweden, Japan, Hungary, Russia |
| Mortality | Longer, healthier lives | Immunisation, maternal care, insurance | WHO programmes, India’s NRHM |
| Migration | Control size and skill of flows | Quotas, points systems, refugee rules | Canada, Germany, Gulf states |
| Distribution | Change where people live | Resettlement, new capitals, growth centres | Indonesia, Malaysia, Brazil |
Population Policies in the World
- Policies differ between developing and developed countries, but each country’s demography and politics give it a distinct path. The common patterns matter more than rigid categories.
Developing Countries
- Since the 1950s, population policy in most developing countries has meant family planning programmes, often begun with foreign aid because of tight budgets.
- A persistent problem is the unmet need for family planning: women who want to avoid pregnancy but use no method.
- Elements of an effective programme:
- Door-step access to good-quality services.
- A wide choice of methods and informed consent.
- Strong information, education and communication.
- Reliable financing, logistics and supplies.
- Monitoring, evaluation and administrative capacity.
- Effectiveness is debated:
- In East and South-East Asia fertility fell fast, sometimes through persuasion or coercion (China).
- In Brazil, fertility fell with little state effort, through urbanisation, female education and television.
- Bangladesh cut fertility from about 7 in the early 1970s to about 2.1 at modest income levels, through home visits by female health workers. This shows that services can work ahead of development.
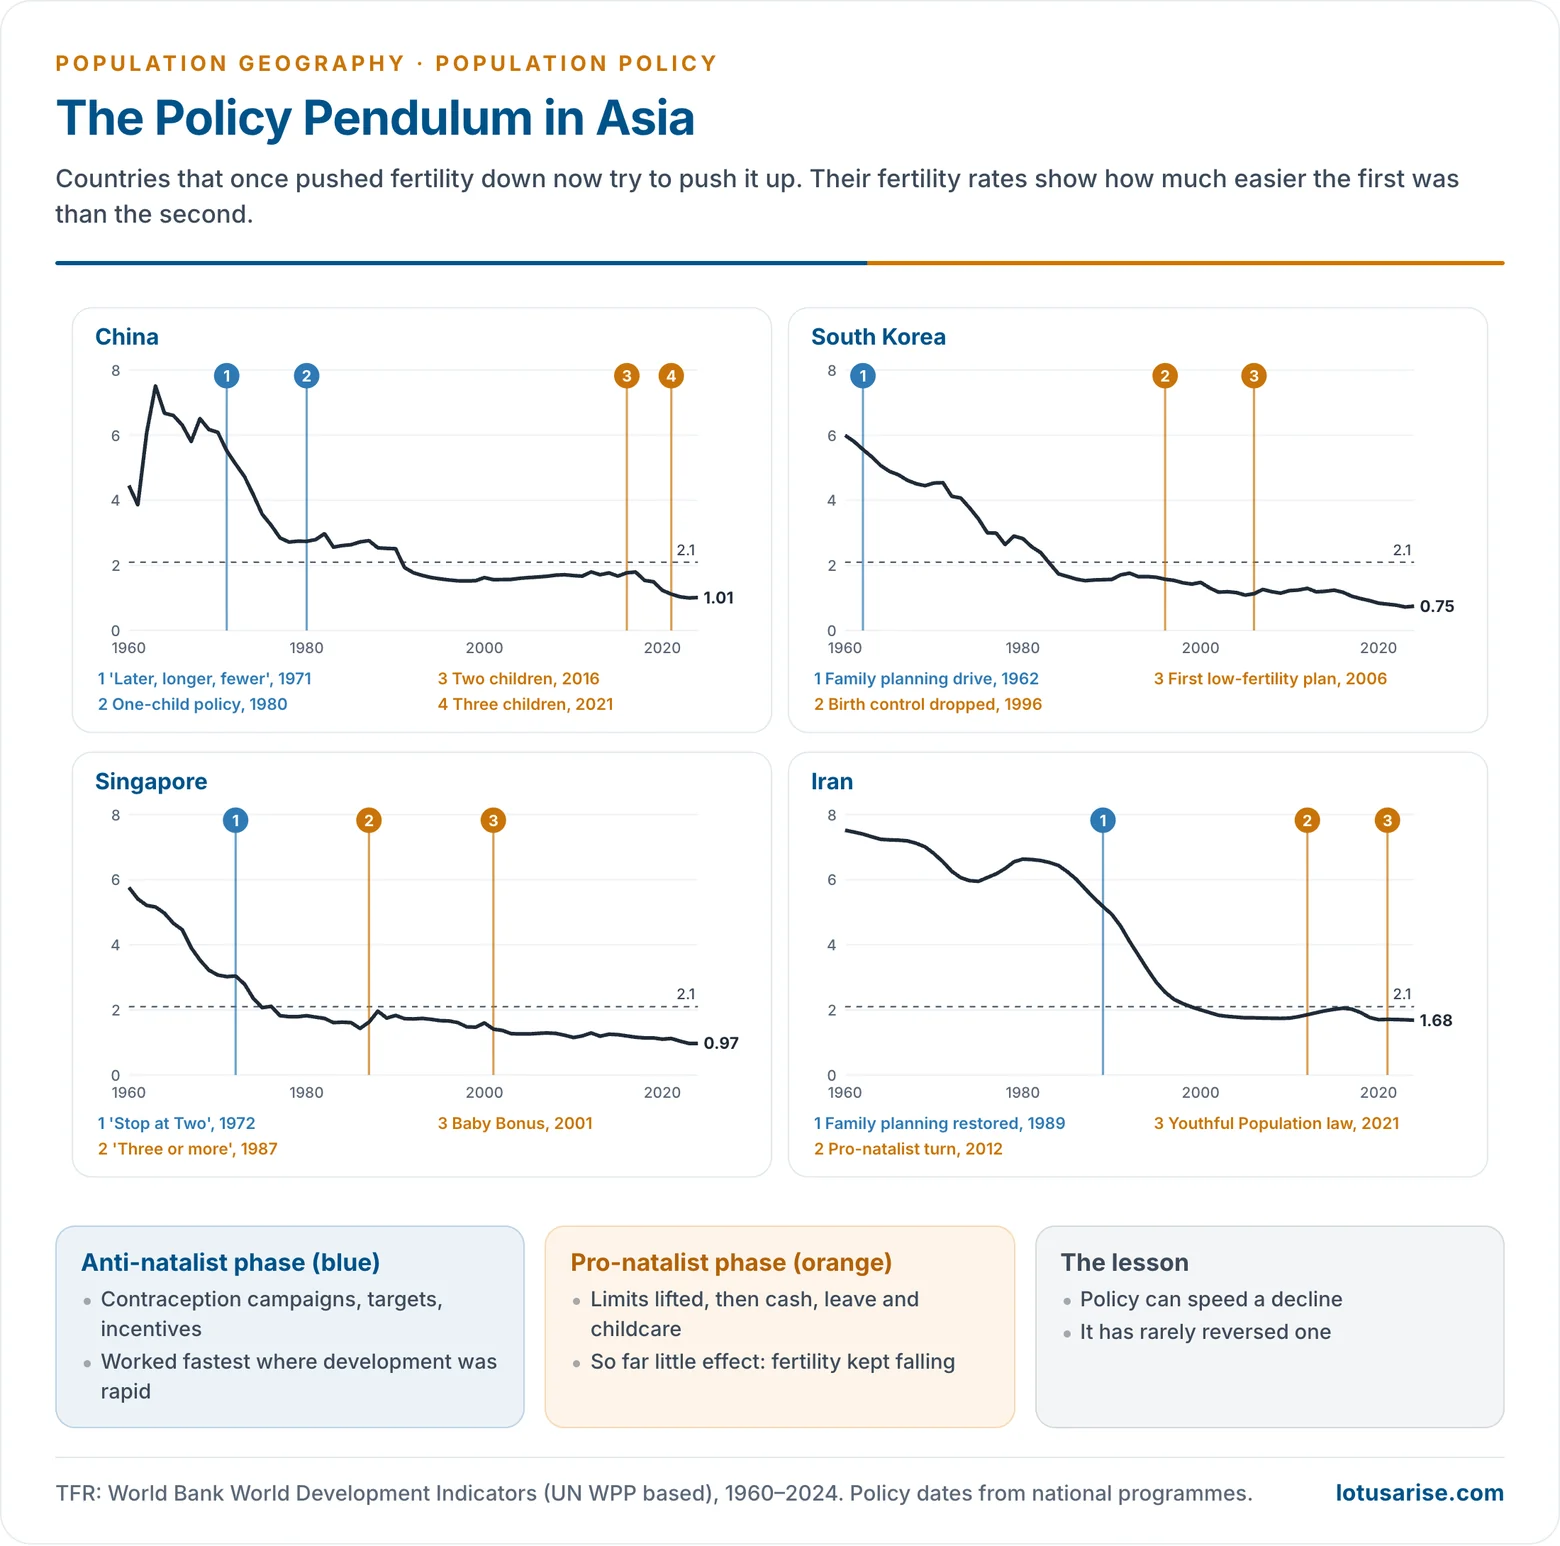
- Iran cut fertility from over 6 in the mid-1980s to about 2 by 2000 through rural health houses and premarital counselling. It then reversed course.
- Weak results usually reflect poor funding, weak delivery and low female autonomy, not a lack of desire for smaller families.
- India was the first country with a national programme (1952). It moved from targets and the coercion of the Emergency to the voluntary, rights-based population policy of India set out in 2000, and reached replacement fertility in 2020.
- After Cairo (1994) the emphasis shifted from contraceptive targets to:
- Maternal and child health.
- Prevention of unsafe abortion and sexually transmitted infections, including HIV/AIDS.
- Women’s education, employment and status, which lower fertility indirectly by raising the demand for smaller families.
- Sub-Saharan Africa is now the main region of high fertility (Niger 5.9, Nigeria 4.4 in 2024). Most of its governments seek lower fertility through family planning and girls’ schooling.
Developed Countries
- Most developed countries have no explicit population-control policy. They influence demography through welfare, health, tax, family and migration policies.
- Low fertility is the main concern:
- Fertility fell early (1920s–30s), rose in the post-war baby boom, and has been below replacement in most of Europe and East Asia since the 1970s.
- The consequences are ageing, a shrinking workforce, high old-age dependency and, without immigration, population decline.
- The rapid ageing seen in age composition data for Japan, Italy and South Korea is the result.
- Policy responses aim to encourage childbearing without coercion:
- Childcare places and pre-school.
- Flexible and part-time work.
- Paid maternity and paternity leave.
- Family allowances and tax relief.
- Immigration, which in practice sustains the workforce of Germany, Canada, Australia and the Gulf.
- Gender and work–life balance:
- A major cause of very low fertility is the “double burden” on women who carry both paid work and most care work.
- The Nordic countries and France kept fertility nearer replacement for decades by making motherhood compatible with employment.
- Where workplaces and families stay traditional (Japan, South Korea, Italy), fertility is lowest.
- East Asia’s reversal:
- Former anti-natalist states now pay for births.
- South Korea, which ran a family planning drive from 1962, dropped birth control in 1996 and has spent heavily on pro-natalist plans since 2006. Its TFR is the world’s lowest (0.72 in 2023, 0.75 in 2024).
- China ended the one-child policy in 2016, allowed three children in 2021 and began a national childcare subsidy in 2025, but its TFR is about 1.0.
- Singapore went from “Stop at Two” (1972) to “Have three or more if you can afford it” (1987) and a Baby Bonus (2001); its TFR is below 1.
- Limits of pro-natalism:
- Incentives tend to change the timing of births more than their number.
- No country has raised fertility back to replacement through incentives alone.
- Cultural change, later marriage, housing costs and job insecurity keep fertility low.
| Context | Main problem | Policy direction | Examples |
|---|---|---|---|
| High-fertility developing | Rapid growth, poverty | Anti-natalist, family planning, girls’ schooling | Niger, Nigeria, Pakistan |
| Transitional | Uneven regional fertility, young workforce | Voluntary family planning, health, skills | India, Bangladesh, Indonesia |
| Low-fertility developed | Ageing, labour shortage | Pro-natalist, work–family balance, immigration | France, Sweden, Japan, Germany |
| Ultra-low fertility East Asia | Fertility near or below 1 | Reversal from anti- to pro-natalist | South Korea, China, Singapore |
Evaluation
- Population policies work best when they go with the grain of development: when they make it easier for people to have the number of children they want, rather than imposing a number.
- Coercive policies (China’s one-child rule, India’s Emergency sterilisations, Romania’s abortion ban) produced short-run results at the price of human rights, distorted sex ratios and lasting distrust.
- Development-led policies, built on female education, health care and old-age security, produced lasting declines (Kerala, Sri Lanka, Bangladesh, Iran).
- Pro-natalist policies have so far slowed but not reversed fertility decline. Ageing societies are therefore turning to immigration, later retirement and higher productivity.
- The shift, in both rich and poor countries, is from “population control” to population management with a human-centred, rights-based approach.




